Friends of Endoscopy
  • Home
  • Quiz Cases
  • Endoscopy Long Cases
  • Short Teaching Clips
  • Blackboard teaching
  • Podcasts
  • Core Reading
    • Basic concepts core reading
    • Gastroscopy core reading
    • Colonoscopy core reading
    • QA core reading
  • About
    • Our sponsors
  • Home
  • Quiz Cases
  • Endoscopy Long Cases
  • Short Teaching Clips
  • Blackboard teaching
  • Podcasts
  • Core Reading
    • Basic concepts core reading
    • Gastroscopy core reading
    • Colonoscopy core reading
    • QA core reading
  • About
    • Our sponsors
Search
Picture
​

Friends of Endoscopy is all about pattern recognition.  See it today and recognise it tomorrow!   Learn from a New Case on most weekdays !!! 
Become a Better Endoscopist ! 

Which diathermy setting?

8/2/2021

 
Picture
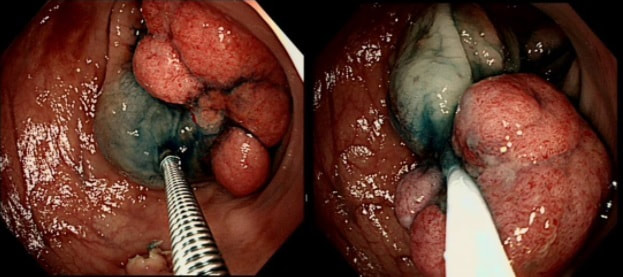
Large polyp at the recto-sigmoid junction on a short stalk which I have pre-injected. 
WHICH DIATHERMY SETTING WOULD BE MOST APPROPRIATE?
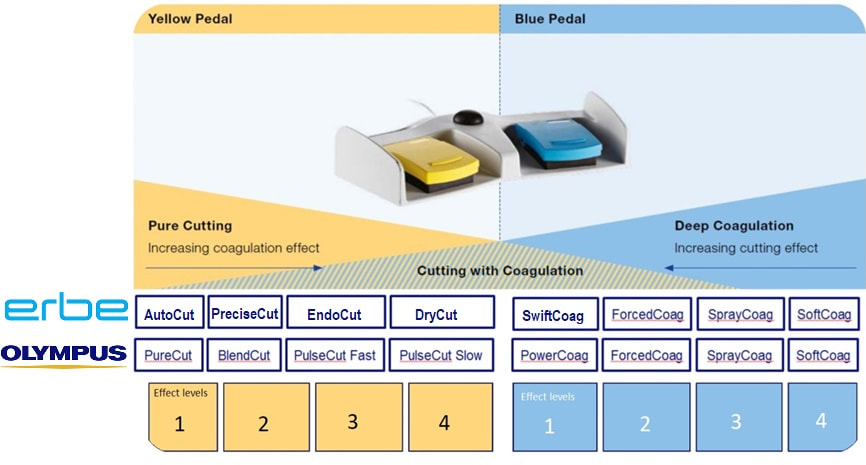
■ Pure cut, effect level 1
it will bleed like stink !
■ A blended cut, effect level 4
Absolutely, steady does it!
■ Coagulation, effect level 1
Too much heat and too little cutting!
■ Coagulation, effect level 4
WAY too much heat and faaar too little cutting!!!
explanation
​Endoscopy is an "art" and there is certainly more than one way of resecting  polyps. A large polyp (turned out to be a TVA+LGD) could only be sustained by a plentiful supply of blood and therefore immediate bleeding is the most important concern.  Removing it piecemeal could reduce the risk of bleeding but would be inappropriate as there is a risk of cancer, nestling deep inside the polyp head. 

As you know, I am not a fan of placing clips beforehand. This is polyp is a good illustration why. A few clips on the stalk would get in the way, may lead the current to the nearby colonic wall and are unlikely to compress the vessels DEEP inside that stalk. 
Picture
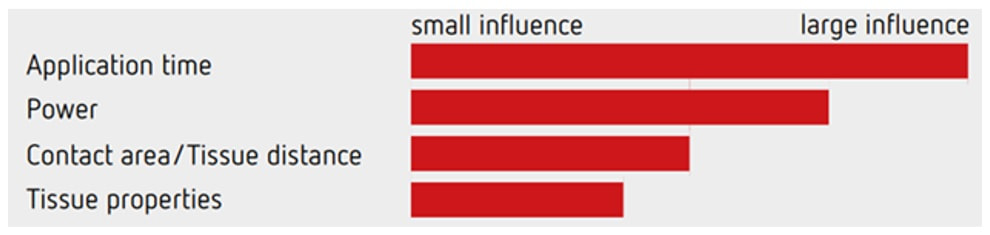
The graph above illustrate the four factors which influence the speed of your cut! The most important is the speed of closing the snare, the second is the power setting of your diathermy, the third is the thickness of your snare (thicker, braided snares take longer to cut through a polyp and will impart more heat) and finally the tissue properties (fatty tissue is slower to cut and I guess that a fat patient will require more electricity for the same about of cutting power). 

Of course you can decide on the speed of snare closure but closing that snare yourself, or asking your assistant to for example count to 10. By the way, a good tip is to ask your assistant to stop applying pressure on the snare handle when the snare is visibly starting to cut through the stalk. In my experience the 'inertia' in the system will continue the snare closure at the correct speed whilst continuing to close the snare handle often cuts the centre too quickly. 

Anyway, this thick stalk could never by cut through with the blue pedal coagulation current.  It's simply too thick and you would end up imparting an enormous amount of heat to the tissues. You may consider 'pre-coagulating' the stalk by first applying some coagulation power and then finish with the yellow pedal.  It sounds clever but I suspect that the last bit which gets 'cooked' is the centre which carries the vessels.  Therefore I hardly ever do it anymore. 

A 'pure cut' (called 'AutoCut' by ERBE and 'PureCut' by Olympus would be inappropriate as it would cut the stalk too quickly leading to immediate bleeding.  You would only use pure cut setting for sphincterotomy, cutting a short oesophageal stricture etc.   This leaves you with the correct answer which is ​B !
Picture

    Categories

    All
    Barrett's
    Cancer
    Cancer Syndromes
    Colitis
    Colorectum
    Corrosive Ingestion
    Crypt Pattern
    Difficulty: Hard
    Difficulty: Moderate
    Difficulty: Very Hard
    Duodenum
    Eosinophilic Oesophagitis
    EUS
    Foveolar Metaplasia
    Gastric
    Gastroscopy
    GI Bleeding
    Histology
    HPB
    Ileum
    Immunosuppression
    Infection
    Local Recurrence Of Barrett's Ca.
    Lymphoma
    Mixed Polyp
    Mucosal Prolapse Syndrome
    NET
    Non-lifting Sign
    Oesophagus
    Opinion Piece!
    Pharynx
    Polyp
    Polypectomy
    The Basics
    TSA

  • Home
  • Quiz Cases
  • Endoscopy Long Cases
  • Short Teaching Clips
  • Blackboard teaching
  • Podcasts
  • Core Reading
    • Basic concepts core reading
    • Gastroscopy core reading
    • Colonoscopy core reading
    • QA core reading
  • About
    • Our sponsors